
Article
HIV and TB: Starting Treatment Is Not Enough. Keeping Patients in Care Is the Real Challenge
RBF 2.0 can accelerate HIV and TB elimination by rewarding sustained treatment adherence, patient retention, viral suppression, and measurable progress across care.
By Results-Based Financing
Shifo Foundation
6 min read
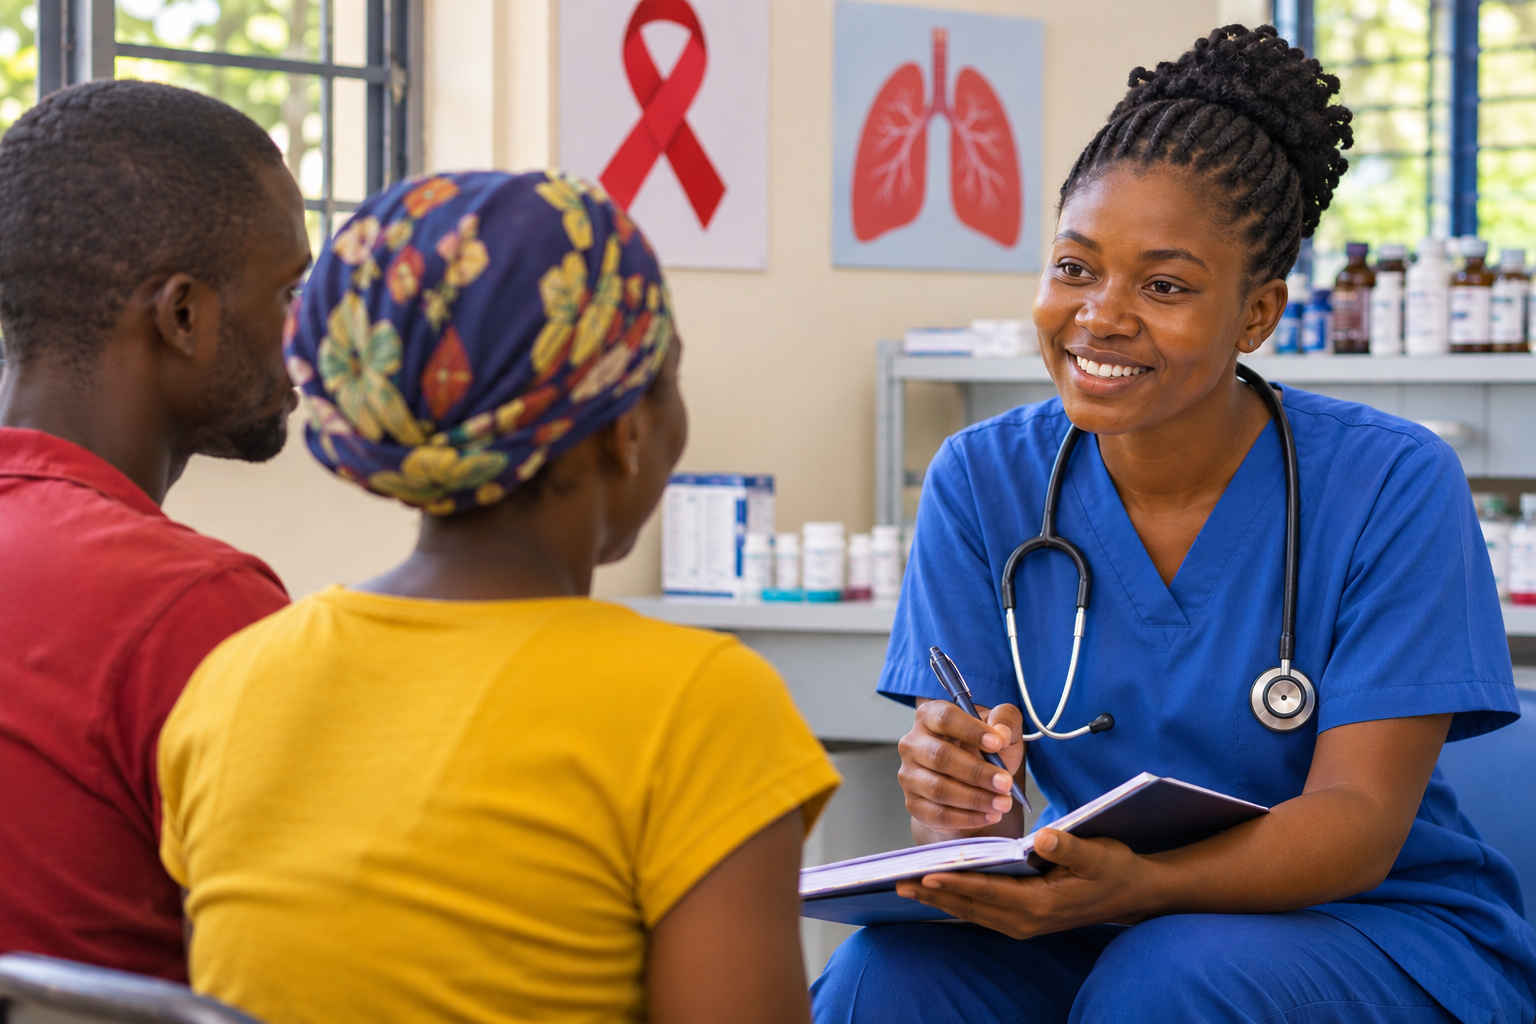
We Know How to Treat HIV and TB. But Can We Build Health Systems That Sustain the Results?
The next frontier in global health financing is not simply getting more people into treatment. It is ensuring they stay there, complete care, and achieve the outcomes that treatment promises. A person tests positive for HIV. They are diagnosed, linked to a health facility and started on antiretroviral therapy (ART). On paper, that is a success. But what happens six months later? Are they still taking their medication? Have they returned for follow-up appointments? Is their viral load suppressed? Can the health facility identify and support patients who have dropped out of care?
The same questions apply to tuberculosis (TB). Diagnosing a patient and initiating treatment are important milestones. But a patient who does not complete the prescribed course remains at risk of poor outcomes, relapse and, in some cases, drug resistance. This is where the next challenge in global health begins.
We have made extraordinary progress in developing treatments, expanding diagnostics and improving access to essential medicines. Yet the distance between making treatment available and ensuring that it works over time remains considerable. The challenge is no longer just about delivering healthcare interventions. It is about building health systems capable of sustaining them.
The problem with counting achievements
Global health programmes have traditionally relied on measurable outputs to demonstrate progress. How many people were tested? How many patients started treatment? How many pregnant women received HIV screening? How many TB cases were notified?
These indicators matter. Without them, there is no meaningful way to measure service delivery. But they do not tell the whole story.
A patient initiated on ART is not necessarily a patient retained in care. A pregnant woman diagnosed with HIV needs continued treatment and support to prevent mother-to-child transmission. A TB patient registered for treatment must be supported until the full course is completed. The distinction is important because HIV and TB are not conditions that can be addressed through a single encounter with the healthcare system. They require continuity, follow-up, reliable medicine supplies, accessible services and sustained patient engagement.
The UNAIDS Global AIDS Strategy 2026–2031 recognises this need, placing greater emphasis on people-centred services, sustainable financing, community leadership and resilient national health systems.
The message is clear: achieving targets is important, but sustaining the systems that make those achievements possible is equally critical.
HIV and TB: The missing link is continuity of care
Consider the HIV treatment journey. Testing is only the beginning. Patients need timely access to ART, regular clinical assessments, viral load monitoring, and support to remain on treatment.
Viral suppression is particularly important. It indicates that treatment is working and that the amount of HIV in the blood has been reduced to an undetectable level. Achieving it requires more than prescribing medication. It requires a functioning system that can support patients throughout their treatment journey.
The same principle applies to preventing mother-to-child transmission of HIV. Identifying HIV during pregnancy is essential, but prevention cannot end at diagnosis. Women need uninterrupted access to ART, follow-up during pregnancy and breastfeeding, and appropriate testing and care for their infants.
TB presents a similar challenge. Treatment completion depends on regular access to medicines, early identification of missed appointments, patient counselling and support to overcome barriers such as travel costs, lost wages and stigma. The WHO End TB Strategy emphasises integrated, patient-centred care, prevention and strong health systems. Its ambition goes beyond treating individual cases to reducing transmission, deaths and the financial burden of TB on affected households.
In both diseases, the outcome depends on what happens between the first visit and the final milestone.
Can Results-Based Financing evolve?
Results-Based Financing (RBF) has helped shift attention towards measurable performance in healthcare delivery. Instead of financing activities alone, it links payments to the delivery of agreed results.
But what if the definition of a result needs to evolve?
Traditional performance-based approaches can place considerable emphasis on individual service delivery milestones. RBF 2.0 offers an opportunity to take this further by rewarding sustained progress across the entire continuum of care. The difference is subtle but significant.
Under a more progressive financing model, a health facility would not be rewarded only for initiating patients on HIV treatment. Its performance could also reflect treatment adherence, patient retention, regular viral load testing and viral suppression. Similarly, TB programmes could move beyond counting diagnosed and registered patients to recognising treatment completion, successful follow-up and appropriate support for patients at risk of interrupting treatment.
For prevention of mother-to-child transmission, performance could be assessed across the full journey, from maternal diagnosis and treatment to follow-up and testing of HIV-exposed infants. This is the central idea behind RBF 2.0: reward not just the achievement of a result, but the consistent progress required to sustain it.
Paying for progress, not just the final milestone
Health systems rarely move from poor performance to excellence overnight. A facility struggling with patient retention may need better tracking mechanisms, stronger community outreach and more consistent follow-up before it can achieve high retention rates.
A rigid, all-or-nothing payment structure may fail to recognise this effort. A progressive approach could recognise improvements along the way. Facilities could receive incentives for moving from lower to higher levels of treatment retention, improving viral load monitoring coverage or increasing TB treatment completion rates. The same thinking could apply to medicine availability, diagnostic services and patient follow-up systems. A facility that consistently maintains essential HIV and TB medicines should be recognised for the reliability it provides to patients.
However, incentives must be designed carefully. Paying for numbers alone can encourage superficial reporting, exclusion of harder-to-reach patients or manipulation of performance indicators. Independent verification, quality checks, equity measures and patient feedback must therefore be built into the financing model.
The World Bank's research on Improving Effective Coverage in Health offers an important lesson. Evidence from performance-based financing programmes suggests that financial incentives alone do not guarantee better outcomes. Transparency, accountability, frontline autonomy and community engagement also matter. RBF 2.0 must therefore be about strengthening the entire delivery system, not simply introducing another payment mechanism.
The role of data in sustaining results
None of this works without reliable information.
Health facilities need to know which patients have missed appointments, which TB patients are approaching treatment completion, which pregnant women require follow-up and whether patients receiving ART are achieving viral suppression. Digital health systems can make this possible by connecting patient records, tracking service delivery and identifying gaps before they become treatment failures. But digitisation alone is not enough. Data must be accurate, timely, and used by health workers to make decisions. Verification must establish that reported achievements reflect actual patient outcomes.
This is where digital infrastructure and performance-based financing can reinforce each other. Reliable data makes accountability possible, while appropriate incentives encourage facilities to act on the information.
From treatment targets to lasting health outcomes
HIV and TB elimination will not be achieved by counting more consultations, tests or treatment initiations alone. It will depend on whether health systems can keep patients connected to care, maintain uninterrupted access to medicines, support treatment adherence and identify problems before patients are lost to follow-up.
The next generation of health financing must recognise this reality.
RBF 2.0 presents an opportunity to move beyond isolated achievements towards sustained performance, where progress is measured across the patient journey and health facilities are supported and rewarded for delivering lasting outcomes. Because ultimately, the success of an HIV programme is not simply the number of people who start treatment. It is the number who remain on treatment, achieve viral suppression and live healthier lives. The success of a TB programme is not just the number of patients diagnosed. It is the number who complete treatment and recover.
We already know much of what it takes to treat HIV and TB. The bigger question is whether we can build health systems that ensure those treatments deliver results, consistently, equitably and over time. That is the shift global health financing must make: from paying for activities to rewarding progress, and from measuring isolated results to sustaining the outcomes that matter.
About the author
Results-Based Financing
Shifo Foundation
Shifo Foundation's Results-Based Financing team works with governments to make performance-linked health financing accurate, timely and transparent.
LinkedInWant to discuss this with Shifo?
Get in touch with our team to talk about Results-Based Financing in your context.
Get in touch